
SuzuKR
SuzuKR
About
- Username
- SuzuKR
- Joined
- Visits
- 0
- Last Active
- —
Comments
-
@Omans said:
https://forum.deadbydaylight.com/en/discussion/comment/3137743#Comment_3137743
The only ones defending nurse in these threads are the exact same 4-5 people, every time. So, yeah, just a few nurse mains. Kind of obvious, actually.
Strange, though. I don't even make posts, and yet different people keep making posts about nurse.
Don't worry. She is exactly like keys and moris. Something only in the game because the devs haven't figured out what to do with her yet.
Which is why devs haven't made any statements on her unlike what they did with Keys and Moris. But yes, clearly.
@Taxman232 said:
I think prior to 6.1 she was fine but the buffs and nerfs from this patch were strongly in her favour. Killers got the base kit buff so she recovers faster after the first hit.
Survivors lost the speed boost post hit, iron will nerfed to oblivion (as a counter), DH nerfed into the ground and DS stun timer reduced now that it is pretty pointless against.
That said, I dont think she needs a Freddy level rework just some rebalancing.
DH is literally better than before against her.
Attack recovery is irrelevant because fatigue overrides it.
The speed boost post hit reduction is basically irrelevant because she has to fatigue and charge anyways, and the difference is mathematically basically negligible if you aren't a killer that can just continue walking normally after a hit.
-
@Omans said:
https://forum.deadbydaylight.com/en/discussion/comment/3137142#Comment_3137142
Watched the first video, hoping for something, anything.
You're joking, right? You show a video of old Dead hard with survivors getting a massive head start in chase so they can get to the only decent area on the map to defend against nurse.
Is that how it has to be? Every advantage given to the survivor in order to survive not even a minute against nurse?
And you use that as "evidence" she is okay?
Tournaments: she is restricted much more than even SWF is in any decent tournament. That‘s just fact.
All these videos are before this patch, which massively buffed her, too. She still okay, yeah? You'll probably play dumb about how this patch massively buffed her, so I'll say it here: Dead hard, super nerf of decisive, less distance after hit and quicker recovery. All of those things buffed nurse WAY more than any other killer received.
You've already been explained all this, anyways. One broken thing being OP (SWF) does not mean nurse should be too.
lmao. Fun fact, knowing where to go to have a better chance against a killer is literally part of skill.
She has a negative success rate in completely unrestricted tournaments if you want to talk comp.
New Dead Hard is even better because Endurance gives more distance than i-frames, which was the only reason DH was good against Nurse.
Quicker recovery is irrelevant to Nurse because fatigue overrides attack cooldown.
You act like it should be expected for a survivor to last an entire minute in a chase as if that's even remotely sustainable design, lmfao.
Get good? I guess.
-
@Brokenbones said:
https://forum.deadbydaylight.com/en/discussion/comment/3137685#Comment_3137685
lol cognitive dissonance my guy we're making posts on a dbd forum it's not that deep, there's no need to act so emotionally invested and start pulling the caps lock and italics out
I call it free because you don't have to do anything to the other survivors for them to get hit with it, the only pre-requisite is picking somebody up which typically isn't hard for Nurse. Then once you're hit by it, you have to either hide or go to the other side of the map. Which yes is the counterplay to avoid getting downed by it but you also cannot do anything useful in that area either. That's what I mean by pressure, the threat of being instadowned just for being within 32m or 40+ meters is huge pressure.
Anyway I'm not interested in playing semantics with you it's kinda pointless.
There are situations where you can't avoid being in Starstrucks range, due to the shape of a lot of maps.
Also you just proved you didn't read my post whatsoever because I quite literally said the phrase: "It's not oppressive on 80% of killers, It's a nurse problem not a starstruck problem".
It's not oppressive on Nurse. Get good.
-
@Brokenbones said:
https://forum.deadbydaylight.com/en/discussion/comment/3137573#Comment_3137573
There are a ton of different reasons you might be near, a lot of maps have corner gens so if the killer happens to hook someone in the center, you quite literally have nowhere to go so stealth is your only option.
Survivors don't know ahead of time the perk is there, you only realise when you're hit with it the first time. A lot of times you simply won't be able to go anywhere.
Idk your argument might as well be "just don't get downed and starstruck will never trigger"
So... do this amazing thing called stay out of that range until the hook happens and then go back in if necessary to do a gen or something? Wow, amazing how that works.
@Brokenbones said:
https://forum.deadbydaylight.com/en/discussion/comment/3137599#Comment_3137599
The problem I have with Starstruck is the perk generates free killer pressure/slowdown just for existing
Like a nurse with a 40M TR picks someone up and now moves from the pickup spot to a hook, anyone within that 40M range is now exposed just because the Nurse picked somebody up. It's 20M but it's a moving 20M which is a lot when you consider how far a surv with agi can be carried
This is why I think stealth is an important way to counterplaying it and SA removes that
The cognitive dissonance is hilarious. "free killer pressure" for using a perk. Quick question, what do you think the word free means? Maybe it's almost like giving up a perk slot for a perk that grants pressure in a specific situation... is supposed to do exactly that? Wow, amazing, who could've guessed? It's almost like that's what equipping a perk is for.
20m is insanely small. Her default TR is 32. With Agitation it's 44 which is only 3s extra of running to get out of the distance.
Gee, it's almost like using a perk that's literally made for anti-stealth is meant to be anti-stealth. Wow, amazing how that works. Gee whiz, it's almost like there's still the most reliable method called DON'T BE IN THE AREA.
@Brokenbones said:
https://forum.deadbydaylight.com/en/discussion/comment/3137624#Comment_3137624
Oh no the free pressure thing applies to the perk itself.
It's just enhanced by perks like Agi and SA, Starstruck on it's own gives free pressure/slowdown
But at least on 80% of Killers, Starstruck isn't as oppressive. Like Nurse IS the problem with this discussion. Maybe you could argue another Killer is just as oppressive with it but I can't think of one off the top of my head
Not sure if you're joking or if you genuinely don't realize Starstruck is a gimmick perk on most characters. But hey, buzzword bingo time, "free" marked off again I guess. So much for knowing what a word's definition is nowadays I guess.
"I didn't leave the area, and so I got affected by the perk that affects said area." Wow, amazing how that works. It's almost like if you literally don't do the counterplay built in, that's on you. If a perk still wasn't useful despite people not doing its counterplay, it would be literally garbage. But yes, it's clearly oppressive because you fail to actually do the counterplay.
-
@Gandor said:
https://forum.deadbydaylight.com/en/discussion/comment/3135314#Comment_3135314
No. It can't.
It's the only killer where survivors can do anything in game and the only thing it does is making it harder for nurse - that's it. For really good nurse - there is literally nothing you can do. Not a single thing. Nada. Zilch.
Also the killer is broken. She can hit you before she materializes from blink, has broken addons, does not get stunned by pallets half the time (sometimes even outside of animations - and yes fatigue should not count) and has largest lounge hits with auto-aim ever (just flick your mouse after blink and you will hit survivor - you don't even need to know where the survivor actually is).
And yes. I mained nurse, but it got too easy recently
@ChuckLit said:
https://forum.deadbydaylight.com/en/discussion/comment/3135314#Comment_3135314
I won't repeat myself. Nurse is not fine, she is the most broken killer in the game right now. On top of that she has insane addons.
I personally wanna see a complete rework to her power. Something like what Freddy got back in 2019.
Sources?
Also pro tip, "I want (insert) to be utterly ruined and alienate its fans the way they did with a previous rework" is not a great take. :)
-
@Brokenbones said:
https://forum.deadbydaylight.com/en/discussion/comment/3137514#Comment_3137514
The perk completely nullifies stealth which is one of Nurse's forms of counterplay, It doesn't matter if she can't see you once the hook happens, if she knows you're in the area close by - she can get you and with Starstruck/Agi it's an insta down
So not only is Starstruck Nurse still as powerful as before, with this perk Stealth is no longer as viable of a method of counterplay meaning running to the other end of the map is the only thing you can do
Or just do what I do and run vigil every game because it counters starstruck
Why are you in the area in the first place? Even without AA you should not be nearby against a Starstruck Nurse who probably will also be bringing Infectious Fright. That is literally on you for making the dumb call of staying there, ESPECIALLY if you're dumb enough to stay in the 20m range.
-
@JPLongstreet said:
https://forum.deadbydaylight.com/en/discussion/comment/3137514#Comment_3137514
I can see Distressing and an offering for Midwich thrown in too being difficult to deal with...
Distressing isn't even good. Midwich is bad design regardless of Nurse. It's extremely tiny, most loops are useless, and it's basically a pure hold-W test, with some of the worst Exit Gate positions for survivors in the entire game.
@CashelP14 said:
When I saw this perk immediately knew I'd hate it. I don't understand why it was ever added tbh.
It should be quite obvious this perk will only be run on Nurse with Agitation and Starstruck. So you added a perk that only suits the most annoying build in the whole game.
Same with the skill check perk. It's only good on the really skilled players. At high ranks survivors don't need perks to make gens go faster.
It literally isn't good though.
-
@Deathstroke said:
https://forum.deadbydaylight.com/en/discussion/comment/3137142#Comment_3137142
Those games were before nurse buff. 90s gens, dh and ds nerf all help her and she didn't need that so only way to compensate that is to nerf her. Range add ons makes nurse easier to use so I think they should kept them and she should be changed more like oni. If she is fine oni should be changed to like her and start with his power.
I don't know why you think I'm a fan of the 90s gens. I explicitly said I'm not a fan of it.
DH is literally stronger against her than before. The reason it was good was the i-frames, which is Endurance instead now which means a successful use gives even more distance.
DS shouldn't have gone down to 3 seconds, it should've stayed at 5s.
Range add-ons and three blinks are busted and should both be reworked.
Oni has instadowns on his power by default, stop pretending like they're even remotely comparable.
-
The complaints over AA are hilariously overblown paranoia.
It has a 20m range. If you are still inside the 20m when the killer stops carrying, there's 2s of extra aura-reading. READ. As in, if you are not in the 20m, there is no lingering aura read.
Nurse fatigue is 3.5s after two blinks into a hit (the standard). Picking up takes 3s. Guess what you can do in that time? Run 26m. You could literally start close enough to physically hug the Nurse, and you would be out of the 20m before the pick up animation even finishes.
Amazing. Wow, so busted.
-
@Pulsar said:
https://forum.deadbydaylight.com/en/discussion/comment/3137404#Comment_3137404
I definitely agree about a better tutorial. Your idea sounds absolutely wonderful.
My point was that the average Nurse is much more experienced (and has more knowledge) than the average Survivor. This, coupled with some very oppressive combo's and a bad matchmaker, make Nurse a complete nightmare everywhere except for the lower and higher levels of play.
I can completely agree with all of this. To be honest, I think slowdown as a whole is a bandaid to what is the true core issue - map and tile design. If big maps were scaled down and tiny maps were scaled up, and tile spawn logic was adjusted to not make super giant dead zones/super giant busted zones, that would in of itself already solve pretty much a huge amount of issues in my opinion. Means chases would be shorter, getting across the map doesn't take an eternity, and by extension, gens are much more manageable, which in turn means things like tunneling/camping could then be nerfed somewhat, because a killer would become way less reliant on ever needing to use those strategies in the first place. The issue is doing all of this would be an absolutely staggering amount of work that would take a huge amount of time and effort. I honestly think the 90s gen change was the wrong way to go about it. I think base regression should be 0.5 instead of the current 0.25, and I think all regression perks should be drastically nerfed and made to only fill specific niches. For example, Pain Resonance lets you know the most progressed gen. Then, base regression is better so just doing chases and whatnot is enough, and "regression" perks only become niche-fulfillment perks.
@Pulsar said:
https://forum.deadbydaylight.com/en/discussion/comment/3137422#Comment_3137422
I'm not asking for a 8K Nurse player to only play against other 8K hour players, that would be unrealistic, as we both know.
I am asking for them not to be given a relatively new player that handicaps the Survivor team in a match that was already going to be difficult.
I agree, I'd love to see more adjustments to the matchmaking system where possible.
-
Thoughts from any BHVR staff would be appreciated. This is still an ever-present issue and the minor factors lost from adding this for accessibility are negligible in my personal opinion compared to the benefits of accessibility.
-
@Pulsar said:
https://forum.deadbydaylight.com/en/discussion/comment/3137399#Comment_3137399
And will this matchmaking issue be fixed?
It's not a fixable matchmaking issue in any game by nature of how it works. In basically any versus matchmaking game ever, the amount of extremely ridiculously good players is very, very small. The odds 5 players are on in DBD all at the same level of skill and in the 4:1 ratio in the same region needed is even smaller. The other option is their queues take literally hours. But it's also not a common issue either, and one that can be bridged with learning more/making it easier to learn by offering guides and tips and whatnot better.
-
@Pulsar said:
I think it's the Frame 1 hit tech, any Nurse mains can confirm?
I figure if she hits you on the first frame possible, it can look funky.
Correct, by swinging before you reappear, you can 'queue' a swing at the first possible frame. However, that obviously carries risks with it because then a successful read from the survivor is automatic unavoidable extra-long fatigue.
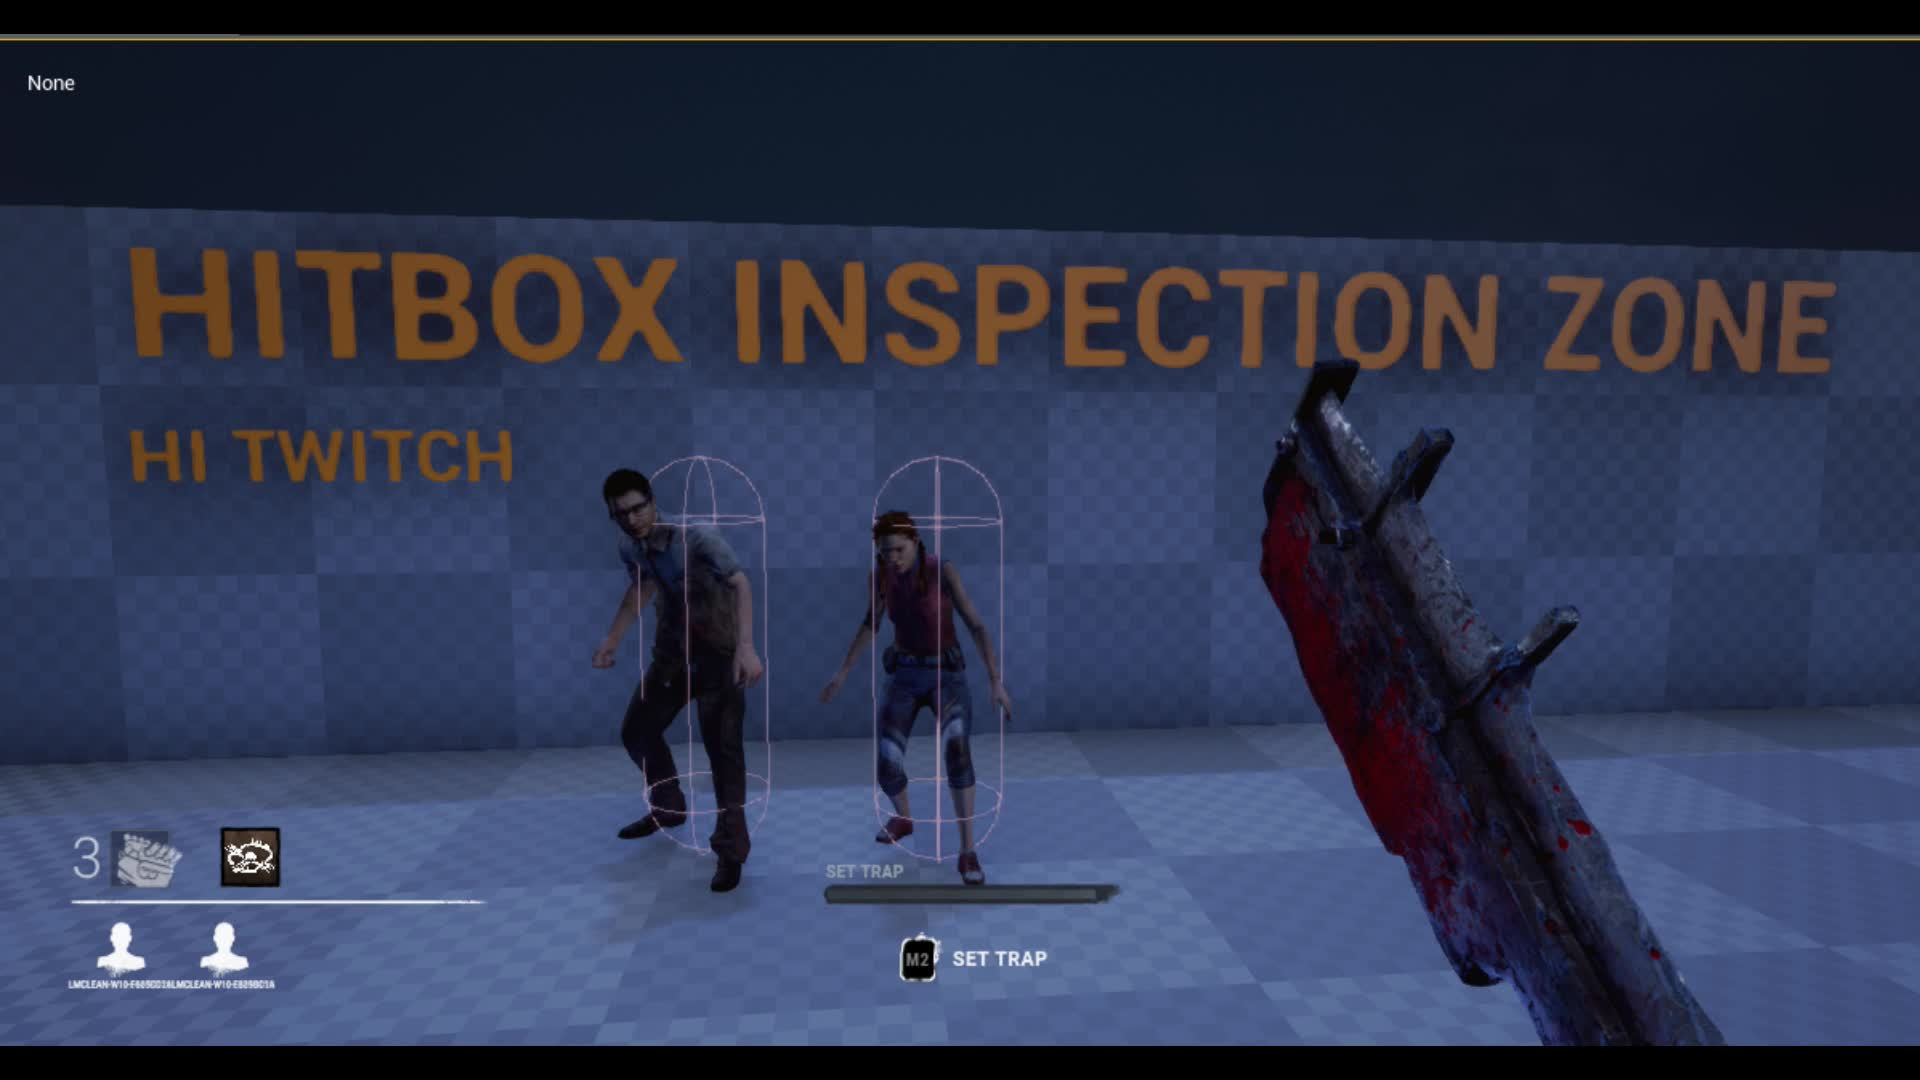
Also, hit validation will ALWAYS look weird on anything super hyper fast because of latency versus the speed itself. For example, Nurse moves up to 13.333m/s during her blink. With 60 ms ping, that is ~0.8m difference. As ping goes up, that goes up even more. Add in that survivors all have the same pill hitbox that doesn't change with animations for consistency, balance, and ease-of-processing sake which is somewhat behind the survivor themselves sometimes/off the visual model, and it'll look even weirder:
-
@threeQuinn said:
https://forum.deadbydaylight.com/en/discussion/comment/3137323#Comment_3137323
He can't do it.. but he can do it. So he can do it? That's why he's #3.
There's a difference in flicking 180 in a single frame and doing it in a multi-step process. One is near impossible to deal with, the other isn't.
-
@Pulsar said:
https://forum.deadbydaylight.com/en/discussion/comment/3137296#Comment_3137296
Well, first off, I believe you've made a fairly interesting leap in judgement. The average Survivor isn't very good and you have assumed that means that the average Nurse player, likewise, is around the same skill level. This is a fairly logical assumption, however, the truth is not so black and white.
As someone who has played a lot of Survivor recently but has played mostly Killer in the past, the average Survivor is hardly able to play around M1 Killers like Myers or Trapper, much less someone like Nurse. Most players understand pallet looping, or window looping but few understand how to mindgame, how to chain tiles, LoS blockers, ect ect. It's why we saw the insanely long 4K streaks in the past, for good players, the game just isn't that challenging. The average player just isn't very good. Likewise, Nurse has a bit of a reputation. She's commonly considered one of the hardest Killers to learn and is very punishing to pick up, whether or not that's true is irrelevant. It deters many players from playing her until they've mastered many other Killers. This puts their skill (game knowledge, map knowledge, mechanical knowledge, ect) at a much higher point than the average Survivor player that they will be likely to match against. These are the most common Nurse players you will find in average MMR.
For example, their builds will usually look something like this:
https://us.v-cdn.net/6030815/uploads/73K4M2KE43T6/nurse-283-29.png
This is what the average player cannot deal with. While the Nurse may be able to be looped for a reasonable amount of time, their perks will help carry them over that shortcoming. These average Nurse's do not have god Blinks. They can be juked and they can absolutely be beaten and they know that. However, the Survivors that they play against do not have the skillset to counter her build, her add-ons, her power and the (generally) more experienced player all at once.
High MMR Nurses will, generally, not stack slowdowns. The Survivors they are going against have both the experience and the toolset to be able to play well against her. The players are generally of equal experience and many high MMR SWF's can deal with the best Nurse's fairly well.
My point is that Nurse is sort of the Killer SWF. For many experienced players, it's perfectly counterable. They might be able to bring certain busted combo's, but other than that, nothing too special. However, not everyone is so experienced and those average players will suffer from a serious power gap.
Thanks for your thought-out response, however I disagree on some of the conclusions. Learning Nurse takes more to play at a minimum level than playing survivor at a minimum level is something I agree completely on, and thus complacency is punished hard. Learning how to deal with standard M1 at average level is enough for most to not need to even try to improve further, which leads to issues like these where people just flat out don't know how to play against more complex killers (not even just Nurse). I agree that average players can struggle at playing against even weaker killers, and particularly solo queue. I think the better decision to go about this would be instead to better the tutorial, and perhaps include things like in-game guides for tips on how to play as and against killers, so there is a better base line of knowledge to learn from for both sides. For example, a looping guide where a survivor practices the correct direction to run a certain tile, and then they're tested in a map without those guides to see if they pick the correct decisions.
Furthermore, I think it's extremely crucial that BHVR closes the gap between solo and SWF as much as possible, not only because of Nurse, but because of so many different issues that is caused from this division. Some killers are kept weak on purpose to not have a power too oppressive for solo despite being weak versus good coordination, some perks or status effects are only really relevant for solo, so on and so forth. By closing this gap as much as possible, it allows BHVR to balance around one single type instead of two distinctly different types of survivor gameplay. I've made suggestions regarding this before, but I think preset message ping wheels that allow for communications of things like "Killer on me"/"Camping"/etc etc as needed would help tremendously in that regard (with minor cooldown to prevent ping spam/ability to mute a specific survivor's pings if they're clearly trolling for example).
I do not think a knowledge gap should be addressed by direct gameplay changes, but rather close said knowledge gap.
-
@Deathstroke said:
Survivors still need something strong to stop tunneling or at least balanced it so that killer loses most games they do that. Ds should be basekit for both hook state with the 3s stun. Perk would make it 5s stun. And the skill check should be automatic or easy so it help new players and I don't have to break my controller to do the skill check.
You are literally advocating that a player should lose most games just for using a strategy. LOL
-
It's a strategy, the base counter is also a strategy: Making use of their lack of pressure on others to slam gens.
You are not meant to have a hard counter to a strategy, that is bad design. Even things like Reassurance can be prevented by killing a survivor before they get close enough to activate it. Hard counters take precedence over skill, which is bad.
-
Maps being closer to a moderate size. Maps like Gideon or Midwich are way too small, maps like Mother's Dwelling are way too large. Ideal size would probably be around Wrecker's Yard's size or so.
Tile spawning logic being improved so busted setups cannot happen anymore. For instance, LTs cannot spawn connected to jungle gyms or shack or main directly. Jungle gyms cannot spawn connected to jungle gyms, shack, or main directly. There cannot be more than 2 connected LTs in a row (no 3 or more in a row).
Adjusting map-specific problems (Gideon having way too many god pallets but basically no helpful windows whatsoever).
The best designed map on average (tile logic aside) is Wrecker's Yard in my opinion.
-
@threeQuinn said:
- Nurse
- Bubba
- Blight, but if Blight was fixed so he couldn't do 180 turns and wall slide, Hag
You do realize Blight can't do a 180 flick in a single turn right? The only way to do 180 now is pre-turn or double-flicks, which are both intentional design. Wall sliding is also an intentional mechanic. I have no clue what you mean by "fix". Only hug tech is unintentional, sliding as a whole is not.
-
@Pulsar said:
https://forum.deadbydaylight.com/en/discussion/comment/3137187#Comment_3137187
Okay.
Let's try this again and start over. I think we've both become to invested and heated, yeah?
Yeah, I'm up for that. My stance is the available proof of good players versus equally good Nurses comes out to be roughly even, both in ability to be chased and the overall game itself (with the exception of things like one-sided maps, people not trying, meme builds. etc).
I think range add-ons and the third blink add-on are fundamentally problematic because they remove or reduce the counterplay available, while I think recharge add-ons are fine or even necessary (depending on the level of play) - not that it's necessary for most levels of play, mostly just the much higher ends. Recharge is less downtime, but doesn't alter the counterplay to any given blink trade attempt itself the way range or the third blink being available does, and base kit recharge time is excruciating against very very good players.
I am of this stance because for both competitive and non-competitive, there is ample evidence that shows said gameplay of those levels of players playing against one another. Furthermore, the amount of extremely good players of anything in any game is a quite small percentage of the player base. The odds an average player will have to even face them in the first place is low, and even if they do, that's on matchmaking and not on balance. Average/okay Nurses will make plenty of mistakes and unsuccessful reads, much the way that average/okay survivors will do the same.
Furthermore, while competitive's results aren't directly relevant to regular DBD, it can still be learned from to see how players at the highest levels of gameplay handle every and any kind of situation. For instance, how one handles chases as or against a given killer (eg, Nurse). And it shows results at the uppermost levels of play, for anyone curious about that. Which in turn would disprove allegations such as "god (insert) is uncounterable and a free win every game", given that very much does not hold out if they actually are matched against equally "god"-like players. Again, the majority of people do not have to worry about this level of play, but even besides results, the gameplay habits and skills can be learned from.
Additionally, confirmation bias is an unavoidable aspect, and most people will not remember wins or average matches to the same extent they remember losses. Furthermore, because she is the best killer in the game, as people get better, it will become more common to face her, which in turn means also having to improve against them to keep up.
Also, fundamentally, I am of the stance she has the best-designed power in the game, precisely because she can ignore physical barriers. It does not matter what tile or location you are at. She cannot brute force a hit the way a standard M1 115% can by walking up to you will eventually do (which is completely unavoidable at dead zones without something like Sprint Burst). She also cannot auto-lose a chase because of any given map design. She must use her power and win at a mindgame to land a hit.
For example, many killers just have areas where their powers do not work well, and they usually must chase as a regular walking 110% or 115%, which is quite disadvantageous, and in stronger tiles, that is usually a point to drop the chase outright as it will not be worth the time it takes to even get a result. Regardless of how much maps are redesigned, this will always be the case because of the variety. However, while additional LoS breakers do make it more challenging, by winning a successful mindgame, she can still play these tiles as well.
Because of this, it becomes almost a virtue in map design as well in some aspects. BHVR does not have to worry about map designs making her busted (other than extremely small map sizes), because tiles do not affect her beyond LoS barriers in the first place. This cannot be said about basically any other killer in this game.
Regarding her power being a basic M1 and thus being able to use Exposed, I don't consider this an issue. Like stated before, mindgaming is built in as counterplay into her kit, and counterplay is built into each individual perk as well that grants Exposed. For example, Starstruck is countered by either already being injured, staying split up from survivors (which would also avoid Infectious Fright), or leaving the area someone goes down by. Yes, it's an issue on small maps, but that is because those maps are too small, not the perk or Nurse itself.
Regarding the myth that she holds back balance or perks, it's quite simple to disprove. BHVR has continually made changes to buff perks or released new perks that are quite amazing on her, which they have never taken issue with. Furthermore, some of the basekit changes such as the survivors running for less time after a hit or the longer gens are also an indirect buff to her. I have no recollection of any such explicit statement from BHVR indicating the opposite.
Regarding how she outperforms every other killer with fairly low downtime compared to them, I am of the mindset people are looking at it the wrong way around. For weaker killers, a single lost trade means they can quite easily lose 20-30+ seconds. That is not sustainable or good design, because that is essentially a lost chase immediately in time-efficiency against better players. Weaker killers also make trades happen much less often because of how long it takes for them to even get in a situation to get a hit each time. Comparatively, Nurse frequently forces trades, and thus constant adaptation and mindgaming. Did you successfully win this trade? Then you bought yourself a modicum of time, and then you will need to do that again. The amount of downtime is much more sustainable design, and it also doesn't go ridiculously long lengths where there cannot be an attempt to land a hit at all that the survivor essentially knows they are completely safe for.
Also, another point is that people underestimate her said downtime. After 2 blinks, if she swings and a whiff, she fatigues for 3.5 seconds. If she doesn't swing, she fatigues for 2.5 seconds (a swing adds +1 regardless of miss or hit). During fatigue, she moves at 0.96m/s. This means that she moves 3.36m in 3.5s or 2.4m in 2.5s, in which time a survivor would run 14m or 10m respectively. Afterwards, she must spend another 2.5 or 3.5 seconds recharging the second blink by default. (3s per token) During that time, she moves at 3.85m/s, and thus would move 9.625m or 13.475m in which time the survivor would run 10m or 14m respectively again. Now both blinks are back,and the survivor is 24m away from the starting location while the Nurse is 12.985m or 15.875m away. While charging a blink, Nurse walks at 2.89m/s, and charging a maximum distance blink takes 2 seconds, which means the Nurse walks 5.78m during that time and the survivor runs 8m during that time, increasing the gap to 13.235m apart or 10.345m apart. In the 1.5s of travel time it takes, the survivor can go up to 6m while the Nurse can go up to 20m. Landing a blink hit with the first hit is extremely unlikely outside of either an amazing read, a survivor misplay, or being trapped into a corner (which is one or both of the previous). The second blink is up to roughly 1.2s or so of charge time, and then up to roughly 1s or so of travel time depending on charge amount. This is where she can attempt to make a hit again or fatigue again. Thus, between the start and this, the following amount of time has passed: 6s to recharge + 2s to charge + 1.5s to travel + [minor to ~1.2s] to charge again + [minor to ~1s] to travel again = A total of 9.5+(minor to ~2.2s) for a total of around 10.5-11.7 seconds. Basically, every won trade will buy around that much time on average.
Regarding the point of her mindgames being difficult, that is the point. Both sides must adapt to the other on the fly based off how the players are reacting and responding to given tools. For instance, if a survivor looks back, that could either be a genuine look back to gauge when to double back, or a bait to fake out the Nurse while running forward. So the Nurse attempts to make a decision based on how the survivor plays when they do that. But if it's inconsistent, it will only be a prediction at best. Likewise in reverse, if the survivor notices the Nurse is looking at a specific location, it might mean that's where they are planning to blink, or a fake to make the survivor think that before flicking. So they judge based off how the Nurse tends to play. Whether they tend to blink short or long on first, how they play around any given tile or location/LoS barrier, etc. Which is what the examples I had shown prove, that said good players understand how to adapt, and prove it is possible. Similarly, the issue at lower levels of play is (1) lack of solo queue communication ability and (2) lack of knowledge both as and against a Nurse.
Regarding the point of "blink to last seen and then readjust", the issue is combined with the above, that is only the most-reliable option. And by this, I mean comparatively so, compared to predicting. However, that does not mean it actually IS reliable in those options. Predictive is a complete guess of where they may go through somewhere you cannot see, which obviously carries a great deal of risk. However, all it takes for an area or a survivor play to throw a wrench into this strategy is for them to cut off LoS somewhere in the time it takes for the Nurse to reach the corner and then make another judgment, either there's another LoS barrier cutting off vision again, or enough distance that the Nurse cannot reach them either way if they attempt to play safely and not predicting. For example, like said before, Nurse has 2s of charge during which she goes 5.78m and the survivor goes 8m, and then 1.5s where she can go up to 20m while survivor goes up to 6m. Something important to note here is it does not matter if the Nurse manually shortens the blink by dragging the mouse down. The blink travel time will always go off whatever the charge amount is. The survivor leaves Nurse's vision prior to or during the charge (which is quite possible at any modicum of distance there will usually be due to Nurse's burst-style of moving during any downtime). For example, running towards Shack. If the survivor simply continues to run and does not attempt to delay any bit, then in the time Nurse reaches the corner, the survivor can make it anywhere from 6-14m away from the given location. Even if Nurse attempts to charge and go for a second blink, she will not land it unless she tries to predictively go through the walls, at which point a double back that beats that prediction will again, evade her. For reference, because of the up to ~minor-1.2s charge time + 0.25-1s travel time of the second blink (minimum blink distance is 1.5m at 6m/s for 0.25s travel, chain blink max distance is 12m at ~roughly 10 or so m/s), as long as the survivor is only not within roughly 6-8m, it denies an extremely small quick follow-up attempt, and longer charges will give even more time to escape said 12m or again avoid wherever she's trying to go.
-
@Pulsar said:
https://forum.deadbydaylight.com/en/discussion/comment/3137142#Comment_3137142
Well, you know, I'm glad that people with 8K hours in Survivor who knows the animations and timing of every Killer can do well against Nurse.
Really, it's good for them.
Unfortunately, 99.99% of the playerbase doesn't know that. I'm honestly pretty much done having this discussion with completely biased and delusional people (who I keep humoring for some reason), so I'm going to head out before I say something I'll regret later lol.
Wow, it's almost like that's why it's a video of someone who's an extremely good Nurse main with thousands of hours. Or do you somehow fail to understand that average players will not be going against insanely absurdly ridiculous Nurses anything more than rarely? Do you think people are facing Seal Team 6 SWFs every time as killer too or something? LMAO
But yes, please stop wasting my time with your bias and delusions if you have no intention of discussing in good faith :) It cycles misinformation and is a detriment to honest discussions. If you ever have actual proof, I'd love to see it. Hint, asserting something is unbalanced because most people are average and do not know how to play as or against something well isn't the way.
-
@TarunCosmo said:
https://forum.deadbydaylight.com/en/discussion/comment/3137134#Comment_3137134
Because it is very common in other games.
Wow it's almost like completely different games are not even remotely comparable.
-
@Pulsar said:
https://forum.deadbydaylight.com/en/discussion/comment/3137105#Comment_3137105
If you can only use your eyes and not your critical thinking ability, then yes.
You don't need to see data to know that Ghostface and Myers are pretty underpowered. You don't need data to see that Doctor is mid. You don't need data to see that 4-man SWF's can be pretty OP. See where this is going?
Hitchens's razor is an epistemological razor (a general rule for rejecting certain knowledge claims) that states "what can be asserted without evidence can also be dismissed without evidence."[1][2][3] The razor was created by and named after author and journalist Christopher Hitchens (1949–2011).Sorry, but you are just wrong, and cases of good players versus other equally good players on Nurse comes out roughly even (outside of one-side favored maps/people doing meme builds or not playing seriously or whatever/etc), both in and out of competitive. Competitive has pretty much all VODs on YouTube and/or Twitch.
As for non-competitive, there's both proof that good players can do just fine in a chase against a good Nurse, as well as that games overall also are roughly even when all skill levels are more or less equal.
Examples of the former: https://www.youtube.com/watch?v=Ig_iQ5S-ABA https://www.youtube.com/watch?v=xnjfG_sLfQg&t=213s (1v1s with SupaAlf, a semi-frequent competitive player and Nurse main)
Examples of the latter: https://www.youtube.com/watch?v=Q_R-gkMwKpA (SupaAlf on MMR Test Day 3 where equal skill matches were prioritized over queue time) https://www.youtube.com/watch?v=o4ZHFVowqws (Fubs vs partial tournament SWF in regular non-tournament KYF) https://www.youtube.com/watch?v=30TKsT-s8Y8 (Ayrun's chases versus a decent Nurse)
The main issue with players of super high caliber is the same issue that exists in any versus game with matchmaking literally ever. There's not enough people of their level on consistently for said even matchups. So they get matched with worse players for the sake of queue times. Which is exactly why good players get massive winstreaks on basically anything and everything. You have solo survivors getting 400+ escape streaks without keys and then stopped counting cause they couldn't be bothered to remember anymore, and people getting anywhere from 50-150+ killstreaks on basically every single killer in this game, like someone playing pre-buff Legion with meme builds and getting over 150 wins in a row when they weren't even trying to go for a streak in the first place and only started keeping count because they noticed they were doing well afterwards.
Good players stomping players that are worse than them is not a balance issue. If it was, literally every single thing in this game would be busted, including solo survivors and even the weakest killers.
-
@Pulsar said:
https://forum.deadbydaylight.com/en/discussion/comment/3137099#Comment_3137099
Nobody can provide that except for BHVR.
Even if I played 2000 Nurse matches in a row, that's still probably less than a single days worth of data that BHVR has access to.
So, there is no proof of her being overpowered.
-
@Pulsar said:
https://forum.deadbydaylight.com/en/discussion/comment/3137073#Comment_3137073
So we should nerf Pinhead, Pig, Freddy ect because of data?
Use your head. Nurse is clearly head and shoulders the best Killer in the game. She's an outlier and a relic from a time long since past.
Nurse's basekit is slightly more reasonable than her add-ons but it is still immensely strong. Don't be willfully obtuse.
Best =/= Overpowered
If you have statistically significant proof that Nurse regularly overperforms against players of the same skill level as the Nurse player, I'd be open to seeing it.
-
@Aneurysm said:
I kind of wish you could pick one killer to have a reduced chance to encounter just for accessibility's sake. Like I do get survivors who quit on learning I'm a plague and although it's mostly not liking her a couple have apologised and said they just can't handle the vomiting. I can't even be mad in that scenario it would just be better to not be matched with them. Yes you'd have to manage how it works with SWF, and yes most people have no specific phobias and will just pick the one they dislike most but I don't see that as such a big deal, there's a lot of other killers out there.
3 is too much especially if there's no restrictions. 4-man squads carefully picking out the 12 strongest killers to avoid would not be healthy for the game at all.
Your idea also contradicts itself. You say it can show which killers are OP and then picked 3 which you don't find OP yourself.
Anyway to eventually answer the question I'd go for clown, bubba and pinhead
Why is your answer that and not just have an accessibility option that replaces Plague's puke with something else visually shaders-wise so it's not puke-like?
-
Have you considered getting over it?
Also your example is not even comparable in the slightest sense. Those games have huge amounts of characters for every type of niche and role, and they are also not a 4v1.
High banrates has nothing to do with balance. People ban for all sorts of reasons. If people don't enjoy playing against a killer, there is no issue.
-
Why would she be nerfed? She's balanced.
-
It literally does not matter if the generator is infected or not. You are still expected to attempt to repair. If the killer comes for you and you get chased off, that's fine. If you refuse to attempt to repair at all, YOU are the problem holding this game hostage.
-
Ignore the people saying blatant misinformation. It is against the rules and can also potentially lead to a ban (read: can; it's a case-by-case basis). It is considered taking the game hostage and refusal to participate in normal gameplay. Taking the game hostage because it is realistically absurd to expect a killer to find people hiding while intentionally avoiding AFK crows. And refusal to participate in normal gameplay, because they are not attempting to progress anything at all. This has been repeatedly and explicitly stated as such by BHVR staff multiple times.
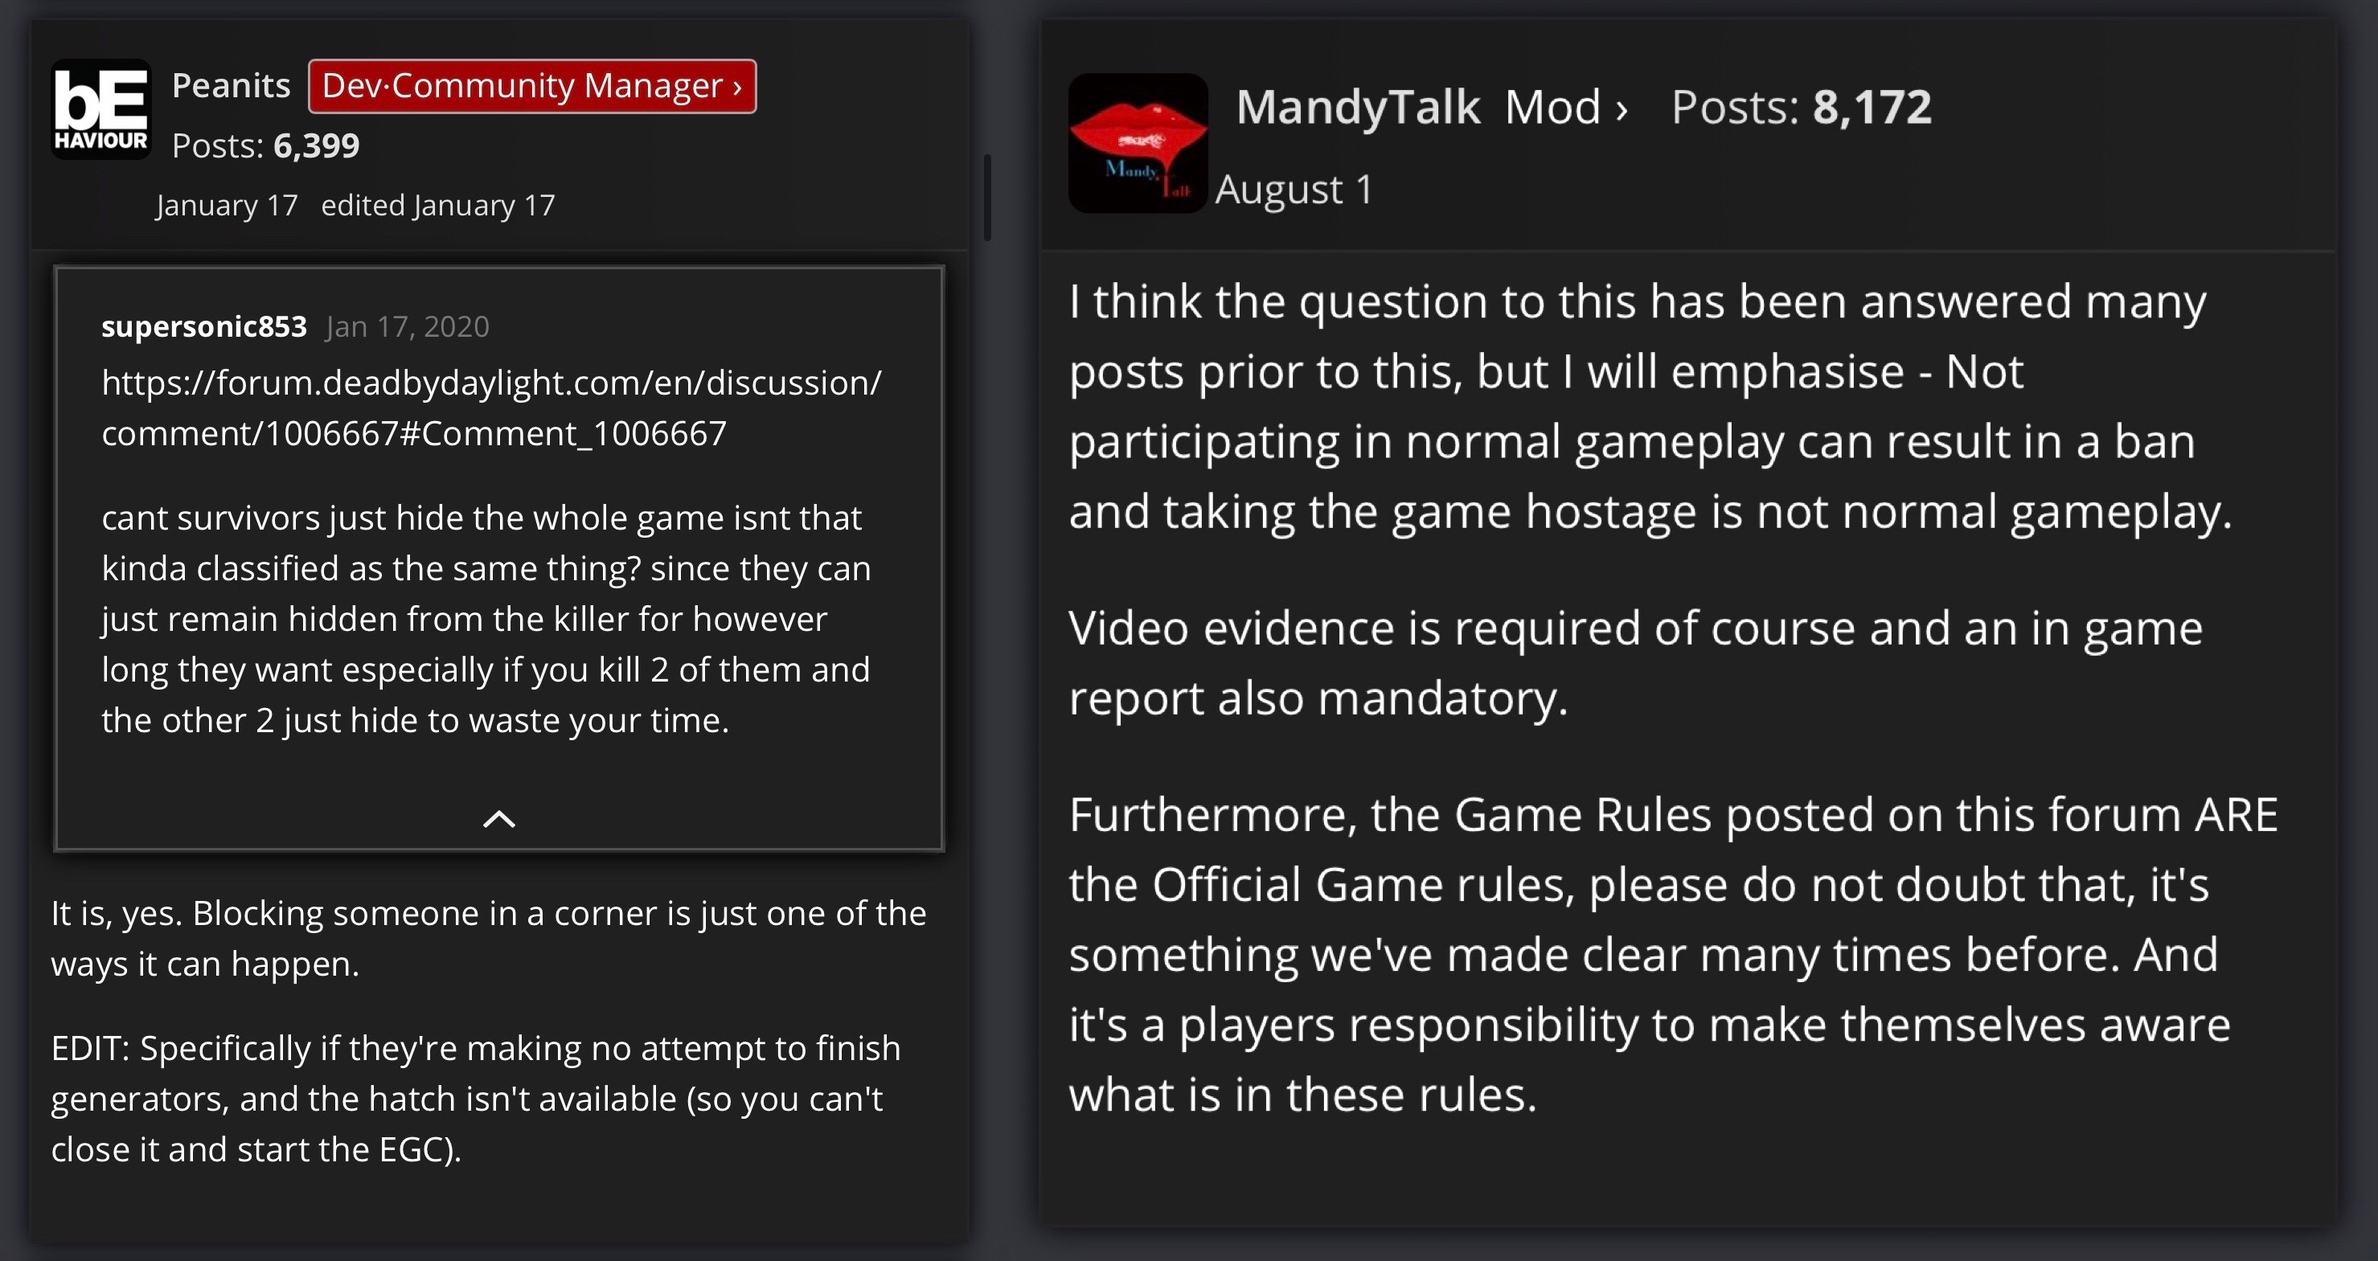
Before someone asks something insanely stupid like "So are survivors expected to just suicide," the answer is no, survivors are expected to attempt to repair generators. Being chased off or occasionally hiding when the killer comes nearby is fine. Refusing to attempt to repair at all is against the rules and can be bannable.
-
Maybe one day people will stop calling using stuff intended to be used as "abuse".
-
Yes, that is literally the point. Congratulations.
-
Clearly, just what this game needs. Even more ways for survivors to suicide out of a match early.
Surrender options can be abused by partying up to never give the random a say. Slugging for 4K is a strat. You can pick them back up or wait out the 4m. The person in question can just tab out or crawl off or whatever.
-
@ChuckLit said:
https://forum.deadbydaylight.com/en/discussion/comment/3135126#Comment_3135126
Well yeah, I agree with the last part. The problem is most killers are nowhere near Nurse's level. And Nurse is the single most overpowered killer in the game.
There are no mindgames involved playing against a Nurse. It's just holding forward and trying to block line of sight. She can still predict your every move if she's a good player and there's little to nothing the survivor can do. She completely ignores pallets, windows, buildings, basic loops, everything.
Why is your answer to nerf the killers doing fine?
Every single thing Nurse can do can be mindgamed, and good players playing as and against her proves that. Prediction is dual-sided. She tries to predict you. You try to predict her. If what you said was true, good players against equally good Nurses would not be escaping around half their matches, which they do.
-
@ByeByeQ said:
https://forum.deadbydaylight.com/en/discussion/comment/3133680#Comment_3133680
I'm not suggesting making all her blink attacks special just the ones on the 2nd blink or later.
Excepting Blight you cannot use Wraith, Onryo, or Clown as examples to defend Nurse having all her blink attacks count as basic attacks. You are comparing the strongest killer in the game to 3 of its weakest. Those killers aren't even B tier. Also if a Clown hits a survivor with a bottle it does count as a special attack, even though it does nothing without Pinky Finger.
As for falling pallets interrupting blinks, how does it already happen? The only case I know of is if the Nurse blinks into where the pallet can be dropped and the survivor drops the pallet once she has actually completed her blink. It's about 50/50 whether or not the survivor gets away without getting hit, the window of opportunity is narrow. I think if falling pallets actually intercepted a Nurse mid-blink then she wouldn't be able to practically ignore pallets as she does now. If a survivor was camping a pallet she could still get the hit by blinking to one side of the pallet and dodging the stun zone.
It does exactly what I think it does. I don't think it would be a net buff or nerf to Nurse really. Sometimes she would be stunned for longer, like in cases where a survivor waits almost until the fatigue is over, and sometimes she would have her fatigue cut short, like if she used 3 blinks and was running Enduring. It would give her reason to run Enduring and it could be fun. Any camera bugs should hopefully be fixed.
Why am I trying to argue with a Nurse main? It doesn't matter what I say, you just don't want your precious main nerfed in any capacity.
Why are you arguing if you refuse to consider it an actual discussion and preemptively dismiss them for being a "Nurse main" as if that invalidates anything?
Also, every single Exposed perk has counterplay built into the perk itself. Nurse blinks have counterplay built into it itself. You have both sources for counterplaying Exposed blink hits.
-
@Coffeecrashing said:
https://forum.deadbydaylight.com/en/discussion/comment/3135097#Comment_3135097
Are you claiming that Nurse’s sustained map traversal speed will be the same? Because that is the very specific thing I am referring to. I care about how long it would take her to blink across a large map, using max ranged blinks.
If you’re actually curious, on average across large distances, it’s about the same as a 115 walking. She does burst and fatigue/charge while the 115 does nonstop steady walk.
-
@BrokenSouI said:
https://forum.deadbydaylight.com/en/discussion/comment/3135105#Comment_3135105
I've been saying that about range. I don't even think they need to be changed entirely. Just reduce the maps. Then reduce the add ons. Maybe to 3 % and 2 %. For a stackable bonus up to 5 % extra traversal.
In my opinion, there are a large number of maps that are too big, and a handful that are too small (Midwich/Gideon/etc), and they should all be readjusted to more moderate sizes (along with any other tile or balance issues such as endless god pallets on Gideon but no decent windows at all).
-
@ChuckLit said:
https://forum.deadbydaylight.com/en/discussion/comment/3132229#Comment_3132229
I do not think her base kit is fine. Nerf her into oblivion, she just ignores basic game mechanics that every other killer has to deal with. I'm sick of going against 50 nurses per day and the chases that last 10 seconds.
Mindgaming is a core mechanic relevant to every single killer in the entire game. If you only last 10s, that’s a you problem or a matchmaking problem. If you want to see other killers, make them more appealing to play.
-
- Requires a totem to be destroyed
- Spawns a totem in the exact same spot
Really? Is it that difficult? This sounds like a solo queue issue.
-
Big maps need their size nerfed. Then range add-ons should be reworked into a different effect during said map rebalancing.
Also Torn Bookmark should be reworked again. Ideally, making her achievement not require 3 blinks so TB can be changed into something that isn't +1 blink. 3 blinks is just bad design fundamentally.
Other than that, everything else is perfectly balanced.
-
Have you considered not behaving like an immature brat instead? How about you don’t suicide/die first hook just cause it’s a killer you don’t like?
-
Helps the Nurse check around the map to see other things while on the way there.
-
I think solo queue is still in favor of killers (both before and after the update), I think pretty much everything else is balanced.
-
@KidDope25 said:
https://forum.deadbydaylight.com/en/discussion/comment/3062326#Comment_3062326
”Stealth” Yet a lot use Infectious, BBQ, Scourge Hook: Floods of Rage, Bitter Murmur, I’m All Ears and soon Wesker’s new perk to make Starstruck even stronger. Plus good nurses know how to find hiding survivors anyway
Infectious - Stay split up
BBQ - Them seeing you is a good thing (takes pressure off the others), otherwise, lockers/being inside the 40m
Floods of Rage - Distortion/Sabotage that hook/don't go down near a Scourge Hook/etc
Bitter Murmur - Bad perk, just get in a locker or something
I'm All Ears - Exploit its cooldown/Distortion/etc, not even super amazing on Nurse compared to others
AA - Literally not good because you can leave the range before they ever get value out of it
-
The healthiest way to reduce it is the way that takes the most work. Reduce big map sizes, adjust tile spawn logic, and that will inherently make chases shorter, and in turn, gens feel less fast. Gen slowdown is just a bandaid for poor map design. The gen increase to 90s and other similar changes are also bandaids.
Furthermore, reducing the need to use those strategies reduces the frequency of their usage. If a killer can do fine without camping/tunneling, then it will happen less commonly. The people that do it regardless will always do it no matter how difficult you make it. Basically, not tunneling/camping needs to be as rewarding or more rewarding than using those strategies.
-
@Deathstroke said:
https://forum.deadbydaylight.com/en/discussion/comment/3133840#Comment_3133840
I block killers who bleed me out and close hatch front of me and hit me again and again on hook I just would hoped I don't have to face these kind of killers again. I don't block if I get tunneled out or facecamped. Well supertunnelers I have blocked but that's it.
Okay? I don't know why you think literally anyone here cares. It doesn't block matching with them, because that's literally the point.
-
Hell no. FNAF can stay out of DBD literally forever.
-
The reason it exists is for the sole and exclusive reason that when the game was tested without it, those that would suicide would just actively sandbag instead (blowing up gens on purpose, trapping teammates in a corner, leading killer over, not hooking, etc). BHVR viewed them suiciding as the lesser evil, since detecting and punishing sandbagging mid-match is near impossible on any sort of accurate level.
-
@Gandor said:
https://forum.deadbydaylight.com/en/discussion/comment/3133983#Comment_3133983
What? I mean.... If games are not about fun. Then why do you play it? Makes absolutely 0 sense to me. The game SHOULD be fun. Ideally for everyone and as much as possible.
https://forum.deadbydaylight.com/en/discussion/comment/3134045#Comment_3134045
Nah. Last 2 are unreasonable to me, but all other items seems legit. I would go for it
Fun is an arbitrary and subjective standard. That is why it's irrelevant. Fun has nothing to do with balance. If something is balanced, it does not matter if some find it unfun. Others find it fun, and neither side's opinion on it matters, because it is balanced. If something is unbalanced, there are objective changes that can be made to balance it further. For instance, changing numbers or adding/removing features. That is not possible for "fun", because everyone has their own opinion and it is not some objective statistic like performance. You will never ever get a situation that is fun for all players all the time. One person's sense of unfun does not trump another's sense of fun, nor vice-versa, which is why balance is the only relevant statistic. Don't like a particular thing? Tough, get over it. Others do. Like a particular thing? Cool, don't care, others don't. Which is why it's not a reason to make changes.
-
The answer to "Should (literally anything that is part of the game on purpose) be removed?" is no. That is how you alienate the playerbase.